Improving Patient Satisfaction Through Better Practice Operations
Patient satisfaction is often treated as a customer-service issue. When scores decline or negative reviews appear, practices may respond with reminders to be friendlier, communicate better, or spend more time with patients.
Those responses can help, but they often address the symptom rather than the underlying problem.
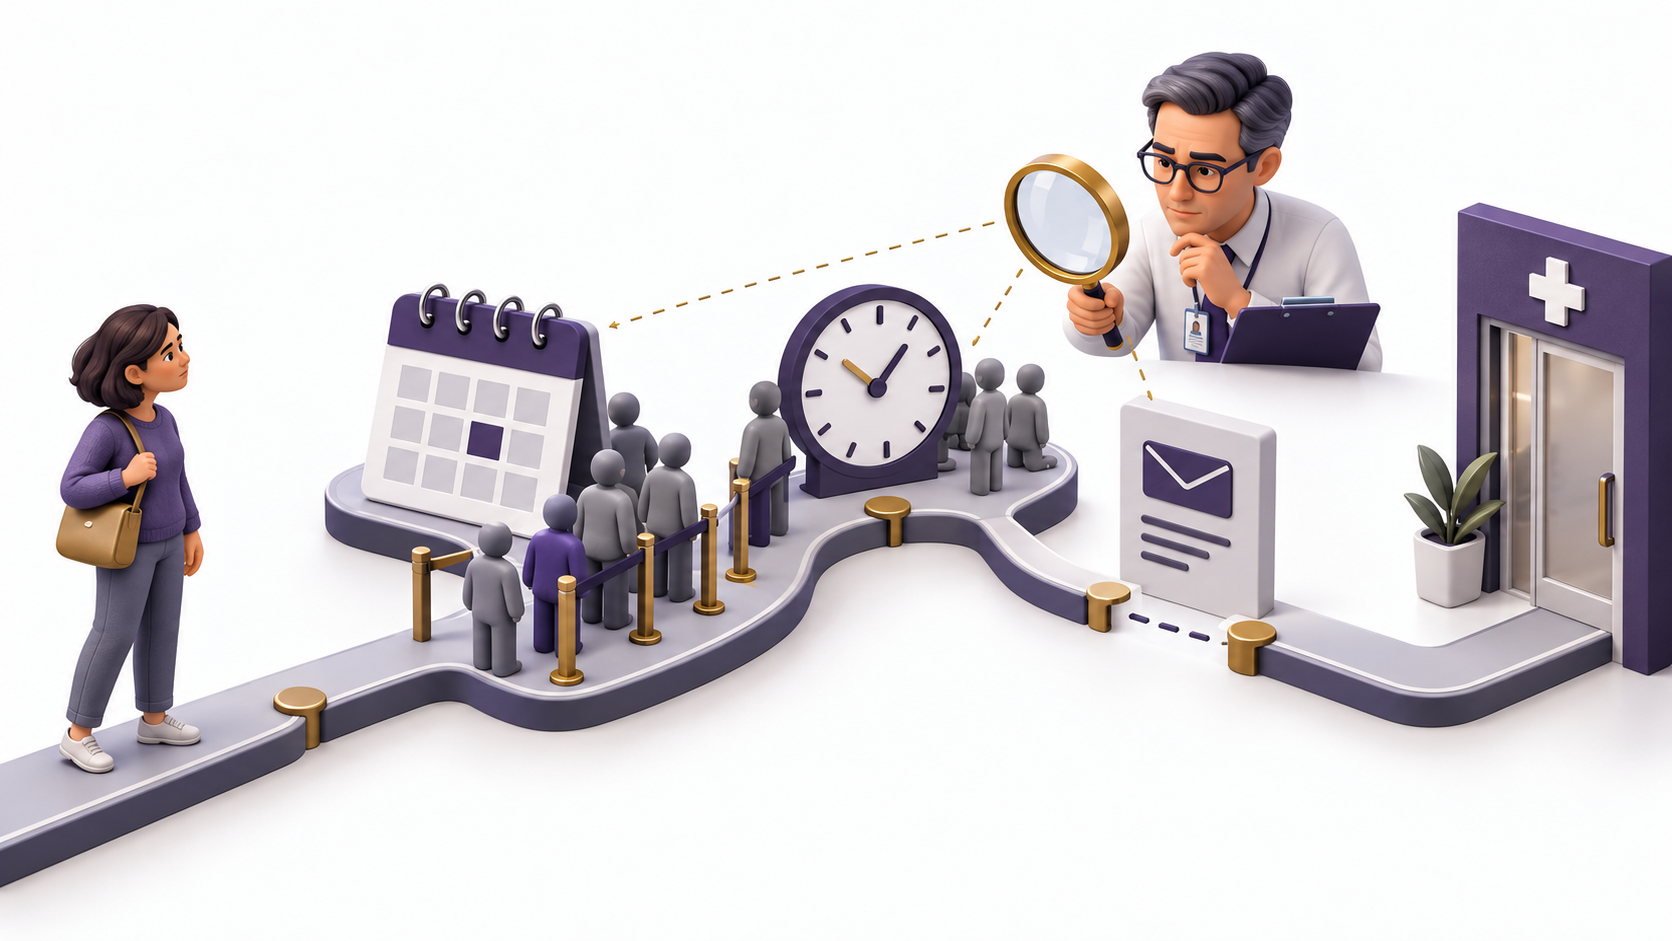
A patient who is frustrated by a 45-minute delay may have encountered a scheduling problem. A patient who repeatedly calls for test results may be experiencing a broken follow-up process. Someone upset about an unexpected balance may be reacting to a financial communication problem that started before the appointment. A patient who feels rushed may be seeing the downstream effect of an overloaded provider schedule.
In other words, patient satisfaction is frequently a reflection of how well the practice operates.
For leadership, the goal should not be to eliminate every complaint or make every patient happy. It should be to understand what the patient’s experience reveals about access, communication, scheduling, clinical workflows, financial processes, and staff performance. Leadership should then correct problems that repeatedly create unnecessary friction.
Operational Snapshot
Recurring patient frustration can function as an early warning signal for operational defects that routine internal monitoring may miss. Leadership can use repeated complaints to identify where capacity assumptions, handoffs, or communication controls are failing before those weaknesses become accepted as normal operations.
Key Takeaways
- Patient satisfaction can reveal operational problems in scheduling, communication, follow-up, billing, patient flow, and other workflows.
- Satisfaction and clinical quality are related concepts, but satisfaction should not substitute for appropriate clinical judgment or quality assessment.
- Recurring complaints are more operationally useful when practices identify patterns instead of reacting to isolated comments.
- Comparing patient feedback with internal measures such as cycle times, response times, scheduling access, and billing inquiries can help identify recurring process problems.
- Clear task ownership, expectation setting, and escalation pathways can reduce avoidable patient uncertainty and repeated contacts.
- Staff behavior remains important, but customer-service training cannot compensate indefinitely for workflows that repeatedly create the same patient frustration.
Table of Contents
Patient Satisfaction Should Not Substitute for Clinical Quality
Practices should be careful about treating patient experience or patient satisfaction as direct measures of clinical quality. Although the terms are often used interchangeably, they are not identical: patient experience focuses on what occurred during care, while satisfaction reflects whether the experience met the patient’s expectations.
A patient can receive clinically appropriate care and still be dissatisfied. The provider may decline an inappropriate medication request, recommend a treatment the patient did not want, or explain that improvement will take longer than the patient expected.
Conversely, a pleasant experience does not automatically establish that the clinical care was appropriate.
The operational objective is therefore not to substitute satisfaction for quality. It is to design the practice so unnecessary frustration does not interfere with good care.
Patients should understand what is happening and what happens next. They should understand how long something is likely to take, whom to contact with questions, and what responsibilities belong to them. When those expectations are clear, practices can maintain appropriate clinical boundaries without creating avoidable dissatisfaction.
Look at Patient Satisfaction Across the Entire Patient Journey
Patient experience begins well before the provider enters the exam room.
A patient may already have interacted with scheduling, registration, eligibility verification, digital forms, the front desk, and clinical support staff. After the visit, the experience continues through referrals, prescriptions, results, billing, follow-up, and future scheduling.
That makes patient satisfaction a cross-functional issue. A problem experienced at one point in the journey may have been created by a decision or workflow much earlier in the process.
| Patient Touchpoint | Common Source of Friction | Operational Area to Review |
|---|---|---|
| Scheduling | Long hold times or confusing appointment options | Access and scheduling workflow |
| Registration | Repetitive forms or insurance problems | Registration and verification |
| Waiting | Unexplained delays | Scheduling templates and patient flow |
| Clinical visit | Feeling rushed or unclear about the plan | Visit workflow and expectation setting |
| Follow-up | No results, referral, or prescription update | Task ownership and care coordination |
| Billing | Unexpected or poorly explained balances | Financial communication and RCM |
| Ongoing communication | Repeated calls for the same issue | Routing and resolution workflow |
Looking at satisfaction by touchpoint gives leadership something more useful than a general instruction to “improve the patient experience.” It identifies where to investigate and which workflow should be examined before the practice assumes the problem is simply employee attitude or customer service.
Expectation Gaps Create Avoidable Dissatisfaction
Many negative patient experiences begin with a difference between what the patient expected and what the practice actually delivered.
Sometimes the expectation itself is unrealistic. More often, however, the practice never established an expectation in the first place.
A patient may not know how long laboratory results typically take. Another may assume a referral will be scheduled automatically. Someone may expect an immediate response to a portal message. A patient waiting in an exam room may not know the provider is handling an urgent clinical situation.
When no expectation has been established, patients fill in the missing information themselves.
That is why expectation setting should be built into operational workflows rather than left entirely to individual communication styles. When expectations depend on which employee happens to answer the phone or room the patient, patients can receive different explanations for the same process.
Operational Snapshot
Expectation setting becomes more reliable when the practice defines what information should be communicated at specific workflow stages. Standardizing those communication points reduces dependence on individual employee judgment. It also gives leadership a process that can be trained, audited, and improved when patients receive inconsistent guidance.
Scheduling staff can explain arrival requirements. Clinical teams can explain how results will be communicated. Referral staff can clarify what the patient should expect next. Billing staff can distinguish an estimate from a final adjudicated balance.
The purpose is not to make promises the practice cannot keep. It is to make the process predictable.
Wait-Time Complaints Should Trigger a Patient-Flow Review
Long waits are easy to interpret as a staff-performance problem. Sometimes they are. Frequently, they reflect how the schedule itself is designed.
If providers routinely run behind, leadership should examine the underlying pattern.
Are appointment lengths realistic for the patient population? Are new-patient visits being scheduled into templates designed for routine follow-ups? Are procedures, urgent add-ons, or complex visits creating predictable delays? Does rooming take longer than the schedule assumes? Are providers absorbing administrative work between patients?
A practice that consistently runs 30 minutes behind cannot solve the problem indefinitely by asking the front desk to apologize more effectively.
Communication about delays still matters. Patients should not sit without information when the practice knows it is running behind. But the long-term solution is to understand why the delay keeps occurring.
Patient complaints about time can therefore provide useful information about scheduling capacity and patient-flow design. Leadership should look for patterns by provider and appointment type. They should also look for patterns by day, time, and workflow stage rather than relying only on general impressions that the office is “running behind.”
Technical Deep Dive
Aggregate wait-time averages can conceal the scheduling conditions that actually produce delays. Segmenting cycle-time data by provider, visit type, session, and workflow stage can reveal whether chronic lateness originates in template design, rooming capacity, visit complexity, or work inserted between scheduled encounters.
Follow-Up Problems Often Reflect Unclear Ownership
The period after the visit is another common source of dissatisfaction.
Patients may be waiting for test results, referral information, medication questions, procedure instructions, or another clinical decision. From inside the practice, several employees may have touched the task. From the patient’s perspective, nothing has happened.
The operational question is not simply whether someone performed each internal step. It is whether someone owns the process through resolution.
If patients repeatedly call for status updates, leadership should examine whether the workflow clearly identifies:
- who initiates the follow-up
- who monitors outstanding work
- what requires escalation
- how completion is documented
- who communicates the final status to the patient
This is where satisfaction data becomes operationally useful. Repeat calls are not only communication events. They can indicate that a workflow lacks a reliable closing step.
A process can appear complete internally because an employee performed an assigned task while still being incomplete from the patient’s perspective. Leadership should therefore evaluate whether the workflow reaches an actual resolution, not simply whether individual tasks were checked off.
Technical Deep Dive
A reliable follow-up workflow needs a closed-loop control, not merely a sequence of assigned tasks. The system should make unresolved work visible until a defined endpoint is reached. A referral, result, or medication question should not disappear simply because one employee completed their portion of the process.
Use Patient Feedback to Identify Operational Problems
A general satisfaction score can tell leadership that patients are unhappy. It may not tell them why.
Effective feedback programs should help the practice identify a process that can actually be investigated.
Questions about scheduling access, wait times, and staff communication can be more actionable than a single overall rating. Questions about clarity of instructions, financial explanations, and follow-up can also be more actionable. Practices looking for a standardized approach to patient-experience measurement can also review AHRQ’s CAHPS Clinician & Group Survey.
The same principle applies to online reviews.
One angry review should not automatically trigger a major workflow change. Patterns matter more.
If multiple patients mention difficulty reaching the office, investigate access. If reviews repeatedly mention long waits, examine scheduling and patient flow. If billing confusion appears frequently, review financial communication and patient-balance workflows. If patients repeatedly say they never received results, investigate clinical follow-up.
Leadership should look for recurring operational signals rather than reacting defensively to individual comments. The value of the feedback is not simply whether it is positive or negative. It is whether repeated feedback helps identify a process the practice can investigate and improve.
Measure Satisfaction Alongside Operational Data
Patient feedback becomes more valuable when it is compared with internal operational information.
If patients report excessive waits, compare those complaints with actual cycle times. If patients say calls are not returned, examine message queues and response times. If billing complaints increase, review the types of balances generating calls. If patients report difficulty scheduling, evaluate call abandonment, appointment availability, and scheduling lead times.
Comparing patient feedback with operational data reduces reliance on perception alone and helps distinguish isolated dissatisfaction from a recurring operational problem.
The objective is not to build an enormous patient-experience dashboard. It is to connect what patients report with what the practice can observe internally.
Operational Snapshot
Patient feedback is more actionable when it is treated as a hypothesis that operational data can test. Pairing a complaint category with the corresponding internal measure helps leadership determine whether it reflects an isolated perception, a measurable process failure, or a problem concentrated in a particular workflow.
Leadership should also look for trends over time. If a particular complaint increases after a staffing change or scheduling-template change, the timing may help identify where the problem began. The same applies after a new communication process or workflow redesign. That gives the practice a stronger basis for deciding what needs to be investigated rather than changing processes based solely on individual comments.
Protect Appropriate Clinical and Operational Boundaries
Patient satisfaction has limits.
Staff should not provide information outside their role simply because a patient wants an immediate answer. Providers should not make inappropriate clinical decisions to avoid disappointing someone. Billing employees should not promise that insurance will pay. Front-office employees should not interpret clinical results because the patient is frustrated about waiting.
A strong patient experience includes boundaries.
Employees should know what they can resolve, what they must escalate, and how to explain that boundary without abandoning the patient.
Compliance Alert
Pressure to resolve a patient’s concern quickly should not push employees beyond defined clinical, financial, or administrative responsibilities. Practices need escalation pathways that let staff preserve role boundaries while keeping the issue moving. This reduces the risk that urgency leads to unauthorized interpretation, commitments, or advice.
“I need our clinical team to review that before we can answer accurately” is very different from leaving the patient without an explanation.
The first protects the workflow and sets an expectation. The second creates uncertainty.
Practices do not have to choose between patient satisfaction and appropriate operational controls. Good systems support both.
Staff Behavior Still Matters
Not every dissatisfaction problem is structural.
Tone, attentiveness, professionalism, and empathy matter because patients experience the practice through its employees. A well-designed workflow can still produce a poor experience if staff appear dismissive or provide inconsistent information.
Training should therefore address both process and behavior.
Employees need to know not only how to complete a task, but also how to explain what is happening when the task cannot be completed immediately.
That is particularly important when patients are already frustrated by pain, financial concerns, delays, or uncertainty.
Leadership should also be careful not to expect frontline employees to absorb the consequences of broken systems indefinitely. If staff spend every day apologizing for the same scheduling delay or answering repeated calls caused by an unreliable referral process, the solution is not another customer-service training session.
The underlying workflow needs attention.
Better Patient Experience Starts With Operational Reliability
Practices cannot control every patient’s expectations, preferences, or reaction to care. They can control how reliably their own systems function.
Scheduling can be designed around realistic capacity. Patients can receive clearer expectations. Delays can be communicated. Follow-up work can have defined ownership. Financial conversations can happen earlier. Staff can be trained to escalate questions appropriately. Feedback can be reviewed for patterns rather than treated as isolated criticism.
When those systems work, patient satisfaction often improves as a consequence.
That is a more sustainable approach than trying to manufacture satisfaction through scripts, amenities, or constant reminders to provide better customer service.
Patient satisfaction is most useful when leadership treats it as information about the practice itself. Complaints, surveys, reviews, repeat calls, and recurring questions can reveal friction that employees may have learned to accept as normal.
Using that information to improve the underlying operation can produce more than a better patient experience. It can support clearer workflows and fewer preventable handoffs. It can also support more consistent staff performance and a stronger connection between operational reliability and quality care.
Frequently Asked Questions About Patient Satisfaction
What is patient satisfaction in a medical practice?
Patient satisfaction reflects how patients perceive their interactions with the practice, including access, communication, wait times, staff interactions, follow-up, billing, and other parts of the patient journey. It can provide useful operational information, but it should not be treated as a direct measure of clinical quality.
How can a medical practice improve patient satisfaction?
Start by identifying recurring sources of patient friction rather than relying only on general customer-service training. Review scheduling, wait times, communication, follow-up, billing, and other workflows associated with repeated complaints. Improving the underlying process can prevent the same problem from affecting patients repeatedly.
Are patient complaints useful for improving a medical practice?
Yes, particularly when complaints reveal recurring patterns. One complaint may represent an isolated experience, while repeated complaints about waits, unanswered calls, billing confusion, or missing follow-up can indicate a workflow problem. Compare patient feedback with internal operational data before deciding what needs to change.
Should patient satisfaction influence clinical decisions?
Patient satisfaction should not replace appropriate clinical judgment or operational boundaries. Providers and staff still need to work within their roles and make appropriate decisions. Practices can support a better patient experience by explaining what will happen next, setting realistic expectations, and providing clear escalation pathways when an immediate answer is not appropriate.
What should a practice measure along with patient satisfaction?
The measures should relate to the problems patients are reporting. Examples include wait and cycle times, message response times, call abandonment, appointment availability, scheduling lead times, repeated patient contacts, and types of billing inquiries. Connecting feedback with operational data helps leadership determine whether dissatisfaction reflects a recurring process problem.
About the Author
Jennifer Blevens-Smith is the founder and principal consultant of Integral Clinic Solutions. With more than two decades of experience supporting independent medical practices, she helps physicians, practice administrators, and healthcare leaders strengthen credentialing, payer contracting, revenue cycle operations, compliance workflows, and practice management. Her work focuses on translating complex healthcare requirements into practical operational processes. These processes improve consistency, reduce administrative burden, and support long-term practice success.
Need Help Strengthening Your Medical Practice Operations?
Integral Clinic Solutions provides practical support for medical practices navigating credentialing, contracting, revenue cycle operations, compliance workflows, front-office systems, and practice management challenges.
Explore more operational guidance, compliance insights, and healthcare business resources on the Integral Clinic Solutions blog. New articles and updates are added regularly for practice owners, administrators, and healthcare teams.
Disclaimer: This content is for informational and educational purposes only and does not constitute legal, coding, billing, compliance, financial, or medical advice. Healthcare practices must verify all operational requirements with applicable payers, regulators, and qualified professionals. Read our full Legal & Compliance Disclaimer.