What Medical Practices Should Know Before Automating Patient Recall
A patient recall system can be operationally sound and still become difficult to manage if the technology supporting it does not fit the practice.
The opposite is also true. A practice can purchase sophisticated communication software with automated texting, campaign tools, scheduling links, and reporting dashboards and still have patients who remain overdue for care. Technology can automate parts of recall, but it does not determine which patients should be recalled. It does not resolve every response or ensure that unsuccessful outreach receives appropriate follow-up.
That distinction matters when practices evaluate patient recall technology.
The objective is not to automate as much communication as possible. It is to use patient recall technology to make a defined recall process more reliable, scalable, and measurable while preserving staff ownership of the exceptions automation cannot resolve.
Key Takeaways
- Define the recall workflow before comparing technology so software capabilities can be evaluated against actual operational requirements.
- Evaluate existing EMR or practice-management functionality before assuming that a separate platform is necessary.
- Treat automated outreach as one part of the workflow; staff still need responsibility for responses, failures, clinical questions, scheduling problems, and unresolved recalls.
- Validate recall populations before campaigns because automation can scale inaccurate selection logic as easily as accurate logic.
- Measure whether patients move from identification through appropriate follow-up rather than relying primarily on messages sent or delivered.
- Train staff on ownership, escalation, exception management, and closure rules in addition to teaching them how to operate the technology.
Table of Contents
Define What Patient Recall Technology Needs to Support
Start With the Recall Workflow Before Evaluating Technology
Practices should define what they expect the technology to accomplish before comparing software.
Recall can involve annual examinations, chronic-care follow-ups, and preventive services, the categories most commonly addressed by reminder and recall systems. It can also involve laboratory monitoring, specialty follow-up, or other services appropriate to the practice. Each may have different eligibility criteria, timing, outreach requirements, and escalation needs.
Technology enters after those requirements are understood.
For example, a system may be capable of automatically generating a list of patients who have not been seen within a specified period. That does not necessarily mean every patient on that list should receive the same message or be scheduled into the same appointment type.
The underlying data and clinical criteria still matter.
A useful technology evaluation therefore starts with questions such as: How are patients identified as due? Where does that information come from? What happens after the first outreach attempt? How does the practice know whether the patient scheduled? What happens when the patient responds with a clinical question instead?
Those questions expose whether the technology supports the workflow or simply sends messages. A platform should be evaluated against the process the practice needs to operate, rather than allowing available software features to define the process after implementation.
Operational Snapshot
Software selection becomes more disciplined when the recall workflow functions as the requirements document. Instead of comparing feature lists in isolation, leadership can test whether each capability supports a defined step, handoff, exception, or outcome—and identify features that add complexity without solving an operational need.
Built-In EMR Tools and Third-Party Systems Solve Different Problems
Many practices already have some recall functionality within their electronic health record or practice management system. Before purchasing another platform, leadership should determine what the existing system can actually do.
Unused functionality is not necessarily missing functionality.
Built-in tools may have an advantage because they already have access to patient demographics, appointment history, clinical information, and scheduling data. Depending on the system, they may support reports and reminders. They may also support patient portal messages or other automated outreach.
Third-party platforms can add capabilities when the existing system is limited, particularly around communication channels, scheduling interactions, campaign management, or reporting. However, adding another system also introduces another workflow and potentially another source of patient data.
The comparison should therefore extend beyond features.
| Technology Consideration | Operational Question | Why It Matters |
|---|---|---|
| Patient identification | Can the system reliably identify the correct recall population? | Poor criteria create missed or inappropriate outreach |
| EMR integration | Does information move between systems accurately? | Reduces duplicate work and inconsistent records |
| Communication channels | Can patients be reached through appropriate methods? | Supports practical outreach without relying on one channel |
| Response management | Where do patient replies go? | Prevents messages from becoming unattended work queues |
| Scheduling capability | Can responses move efficiently into scheduling? | Reduces unnecessary handoffs |
| Reporting | Can the practice track outcomes, not just messages sent? | Makes recall performance measurable |
A platform with more features is not automatically the better operational choice. Integration and usability often matter more than the length of the feature list. Leadership should also consider whether adding another platform creates duplicate work, fragmented records, or additional queues that staff must monitor.
Technical Deep Dive
A third-party platform’s true workload includes the interfaces and reconciliation tasks created around it. Evaluate where patient status, scheduling activity, replies, and final dispositions become authoritative; otherwise, staff may spend the time saved by automation correcting duplicate records or monitoring parallel queues.
Use Automation Without Losing Accountability
Automation Should Reduce Repetitive Work, Not Remove Accountability
The strongest use case for recall technology is repetitive administrative work, which is consistent with MGMA’s 2026 patient-access survey, where practice leaders named automated reminders and confirmation texts as their leading response to no-shows.
Software can generate lists, send standardized outreach, and record delivery attempts. In some cases, it can also allow patients to request or schedule appointments. That can reduce the number of individual calls staff must initiate.
But automation creates its own work queues.
Patients may reply that they already completed the service elsewhere. They may say they changed practices. A scheduling link may not offer an appropriate appointment. A message may be undeliverable. A patient may respond with a clinical concern. Another may repeatedly receive outreach without taking action.
Someone must own those exceptions.
A practice should define where responses are routed and how frequently queues are reviewed. It should also define which responses require clinical escalation and when automated outreach transitions to manual follow-up, creating the operational safeguards needed to keep the process reliable.
The practice should also define what counts as resolution. A message being delivered is not the same as the patient completing the needed follow-up. Without a defined endpoint, an automated process can appear successful while unresolved work accumulates elsewhere and patients remain overdue.
Operational Snapshot
Automation changes the composition of recall work rather than eliminating it. As routine outreach decreases, exception handling becomes a larger share of staff responsibility, so implementation planning should account for queue volume, response expectations, escalation capacity, and the employees authorized to resolve nonstandard cases.
Two-Way Communication Changes the Staffing Requirement
One-way reminders are relatively simple operationally. The system sends information, and the patient takes a separate action if they want to respond.
Two-way messaging changes that workflow.
Allowing patients to reply can make recall more convenient. The patient may be able to ask a scheduling question, request an appointment, or indicate that the service is no longer needed. But every response creates work that must be reviewed and routed.
That means two-way texting should not be evaluated only as a patient-engagement feature.
Leadership should determine who monitors incoming messages, what response times are expected, how scheduling requests are handled, what happens when clinical information is included, and how communication is documented when necessary.
A patient who includes a clinical concern in a recall response has moved outside the standard administrative pathway. Staff need to recognize that transition and route the message according to the practice’s clinical communication and escalation procedures.
A communication feature is valuable only when the practice has a workflow capable of managing the communication it generates.
Operational Snapshot
Enabling replies effectively creates a new inbound service channel. Before activating two-way messaging, leadership should treat monitoring capacity, coverage during absences, routing rules, and response expectations as implementation requirements—not operational details to solve after patient messages begin arriving.
Make Sure Automation Targets the Right Patients
Campaigns Require Reliable Patient Selection
Campaign messaging can extend recall beyond individual reminders by allowing a practice to contact groups of patients who meet defined criteria.
That can be useful for preventive services, seasonal outreach, chronic-care follow-up, or other targeted needs, and a Cochrane systematic review of reminder and recall interventions found they reliably increase the share of patients who complete recommended care.
The operational risk is assuming that a report automatically represents the correct patient population.
Before launching a campaign, practices should understand how patients are being selected. Depending on the purpose, criteria may involve age, diagnosis, and appointment history. They may also involve procedure history, laboratory information, or other documented data.
The list should also account for patients who should not receive the message because they already completed the service, transferred care, declined further outreach, or otherwise no longer meet the criteria.
This makes list validation an important control point. A technically successful campaign can still create operational problems if the underlying population is inaccurate. The more automated the campaign, the more important the underlying data becomes.
Automation scales good selection logic. It also scales bad selection logic.
Technical Deep Dive
Treat recall population logic like a production rule that requires validation before deployment. Reviewing both who is included and who should be excluded can catch stale completion data, inaccurate status fields, or poorly defined criteria before a configuration error is multiplied across an entire campaign.
Build a Hybrid Recall Process for Nonresponders
Not every patient will respond to a text, portal message, email, automated call, or scheduling link.
That does not mean the technology failed.
It means the practice needs to decide what happens next.
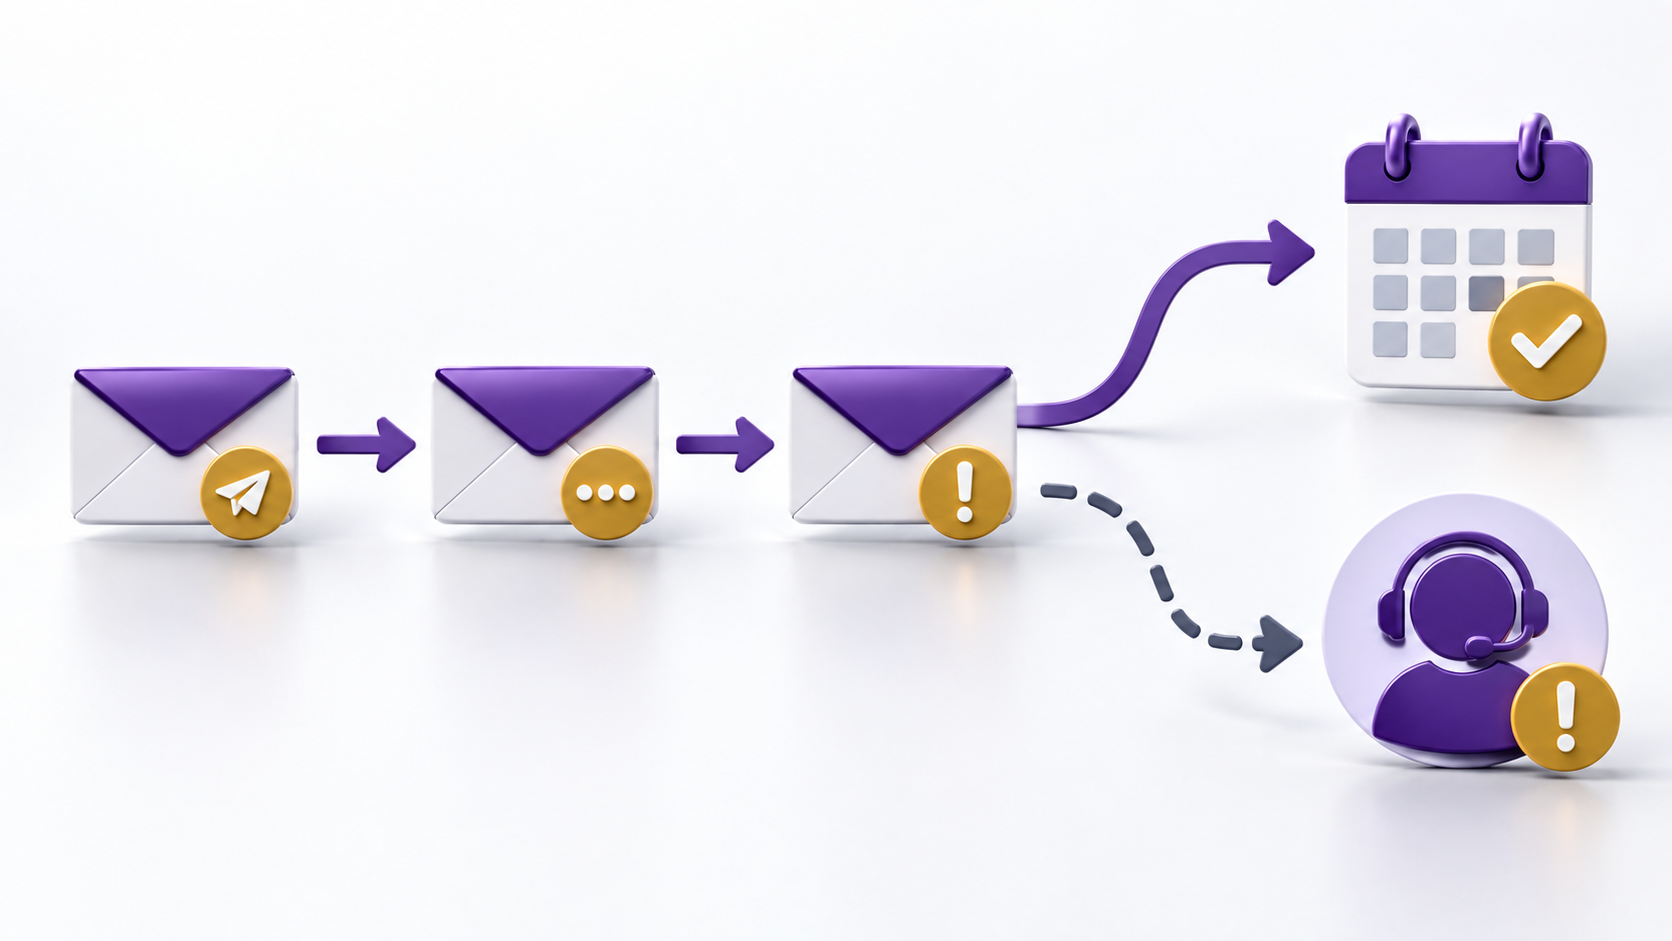
A practical patient recall technology workflow may include:
- automated identification of patients meeting established recall criteria
- initial outreach through the practice’s selected communication channel
- automated or staff-assisted scheduling for patients who respond
- an exception queue for failed messages, questions, or unresolved responses
- defined manual follow-up for patients who meet the practice’s escalation criteria
- documentation of the final disposition when the recall cycle is complete
This approach uses automation where it creates efficiency while reserving staff effort for situations requiring judgment or additional intervention.
It also prevents the practice from repeatedly sending automated messages without knowing whether the underlying recall need was resolved.
The practice should define when automated outreach ends and when manual follow-up begins. It should also define when the recall cycle can be closed. Those decisions may differ depending on the type of care involved and the practice’s established recall policy.
Operational Snapshot
A recall system needs a terminal status, not just a sequence of outreach attempts. Defining how completed care, transfer, documented disposition, escalation, and other valid endpoints are recorded allows leadership to separate genuinely closed recalls from patients who simply reached the end of an automated message sequence.
Measure Whether Patient Recall Technology Resolves the Work
Measure Resolution, Not Just Message Activity
Technology vendors can provide substantial communication data, but not every metric tells leadership whether the recall process is working. This distinction is also reflected in national quality frameworks such as HEDIS measures, which track completed preventive and chronic-care services rather than outreach volume.
Messages sent and messages delivered describe activity.
The more meaningful question is what happened afterward.
Practices should be able to determine how many patients were identified for recall and how many were successfully reached. They should also be able to determine how many were scheduled, how many completed the intended follow-up, and how many remained unresolved.
That distinction helps leadership separate communication performance from recall performance. A high message-delivery rate may show that contact information and the communication channel are working. It does not establish that patients completed the care the recall process was intended to support.
Staff effort matters as well.
If a new platform sends thousands of automated messages but creates a large inbound queue that staff cannot manage, the technology may have shifted work rather than reduced it. If appointment volume increases but inappropriate scheduling also increases, the configuration may need adjustment.
Operational Snapshot
Technology ROI should account for downstream labor, not just outbound automation. If higher outreach volume produces more replies, scheduling corrections, clinical escalations, or exception handling than staff can absorb, the practice has increased process capacity at one stage while creating a bottleneck at another.
Performance should be reviewed as a workflow, not merely as a communication campaign.
Review the System as Patient Needs and Workflows Change
Recall technology should not be configured once and then ignored.
Patient contact information changes. Staff responsibilities change. Appointment types change. Clinical workflows evolve. New communication features may be added. Reports that once identified the right patients may no longer reflect current practice operations.
Periodic review should therefore examine both technology performance and workflow performance.
Leadership should look for patients being contacted unnecessarily, recall populations that appear incomplete, aging response queues, scheduling bottlenecks created by campaigns, and manual work that could reasonably be automated.
The review should also confirm that responsibility for key queues and reports still matches current staffing. A process that worked because one employee knew how to manage exceptions can become unreliable when roles change unless that responsibility is documented and transferable.
The goal is not constant optimization for its own sake. It is ensuring the technology continues to support the recall process the practice actually needs.
Technical Deep Dive
Recall configurations can drift even when the software itself is functioning correctly. Periodic validation should test whether population logic, appointment mappings, queue ownership, communication settings, and closure rules still match current operations, especially after staffing, scheduling, or clinical workflow changes.
Train Staff to Manage Recall Exceptions
Technology training often focuses on where to click.
Staff learn how to run a report and launch a campaign. They learn how to send a message or view a dashboard. Those skills are necessary, but they do not explain how the practice expects the recall process to operate.
Employees also need to understand what to do when something does not follow the standard path.
Who reviews unsuccessful outreach? Who corrects inaccurate patient information? What happens when a patient says the service was completed elsewhere? Who handles clinical questions? When should outreach stop? Who determines whether a patient remains on the recall list?
Those decisions should not be left to individual employees to interpret differently.
Training should connect the technology to the practice’s recall policy and workflow. Staff should understand how to use the system. They should also understand what they own and what they can resolve. They should understand what must be escalated and how completed work is documented.
Frequently Asked Questions About Patient Recall Technology
What should a medical practice look for in patient recall technology?
A practice should evaluate whether the technology can identify the appropriate recall population, integrate with existing systems, support useful communication channels, manage patient responses, connect with scheduling, and report meaningful outcomes. The best fit is the system that supports the practice’s defined recall workflow rather than simply offering the most features.
Should a practice use its EMR recall tools or a third-party system?
Start by determining what the existing EMR or practice management system can already do. A third-party platform may add useful communication, scheduling, campaign, or reporting capabilities, but it can also create another system and work queue. Compare integration, usability, workflow impact, and reporting needs rather than features alone.
Can patient recall be fully automated?
Automation can handle repetitive tasks such as identifying patients, sending outreach, and recording delivery attempts. Staff still need to manage exceptions, failed messages, clinical questions, scheduling problems, inaccurate patient information, and unresolved follow-up. A reliable recall process combines automation with clearly assigned staff responsibility.
How should a practice measure whether patient recall is working?
Measure outcomes in addition to communication activity. Practices may track patients identified, patients reached, appointments scheduled, follow-up completed, unresolved recalls, and staff workload. Messages sent and delivered can help evaluate communication performance, but they do not show whether the underlying recall need was resolved.
What should happen when a patient does not respond to automated recall messages?
The practice should have a defined nonresponse workflow. That may include additional automated outreach, manual follow-up, escalation based on established criteria, and documentation of the final disposition. The appropriate process may differ by the type of follow-up involved and should be established in the practice’s recall policy.
Patient Recall Technology Works Best as Infrastructure
Patient recall technology should make it easier for a practice to identify patients who need follow-up and conduct appropriate outreach. It should also make it easier to manage responses and determine whether the recall was resolved.
It should not become a substitute for defining those responsibilities.
The most effective systems combine automation with clear operational ownership. Technology handles repetitive work at scale. Staff manage exceptions, judgment, escalation, and unresolved follow-up. Reporting gives leadership visibility into whether patients are actually moving through the process.
When those pieces are connected, patient recall technology becomes more than a messaging tool. It becomes infrastructure supporting continuity of care and a more manageable administrative workflow.
That is the standard practices should use when evaluating patient recall technology: not how many features the platform offers, but whether it helps the organization run a reliable recall process from identification through resolution.
About the Author
Jennifer Blevens-Smith is the founder and principal consultant of Integral Clinic Solutions. With more than two decades of experience supporting independent medical practices, she helps physicians, practice administrators, and healthcare leaders strengthen credentialing, payer contracting, revenue cycle operations, compliance workflows, and practice management. Her work focuses on translating complex healthcare requirements into practical operational processes. These processes improve consistency, reduce administrative burden, and support long-term practice success.
Need Help Strengthening Your Medical Practice Operations?
Integral Clinic Solutions provides practical support for medical practices navigating credentialing, contracting, revenue cycle operations, compliance workflows, front-office systems, and practice management challenges.
Explore more operational guidance, compliance insights, and healthcare business resources on the Integral Clinic Solutions blog. New articles and updates are added regularly for practice owners, administrators, and healthcare teams.
Disclaimer: This content is for informational and educational purposes only and does not constitute legal, coding, billing, compliance, financial, or medical advice. Healthcare practices must verify all operational requirements with applicable payers, regulators, and qualified professionals. Read our full Legal & Compliance Disclaimer.